Food Allergies Cannot Be Ignored; They Might Have a Life-Threatening Effect Upon Treatment

Marc Leffler, DDS, Esq.
July 28, 2025

Reading time: 8 minutes
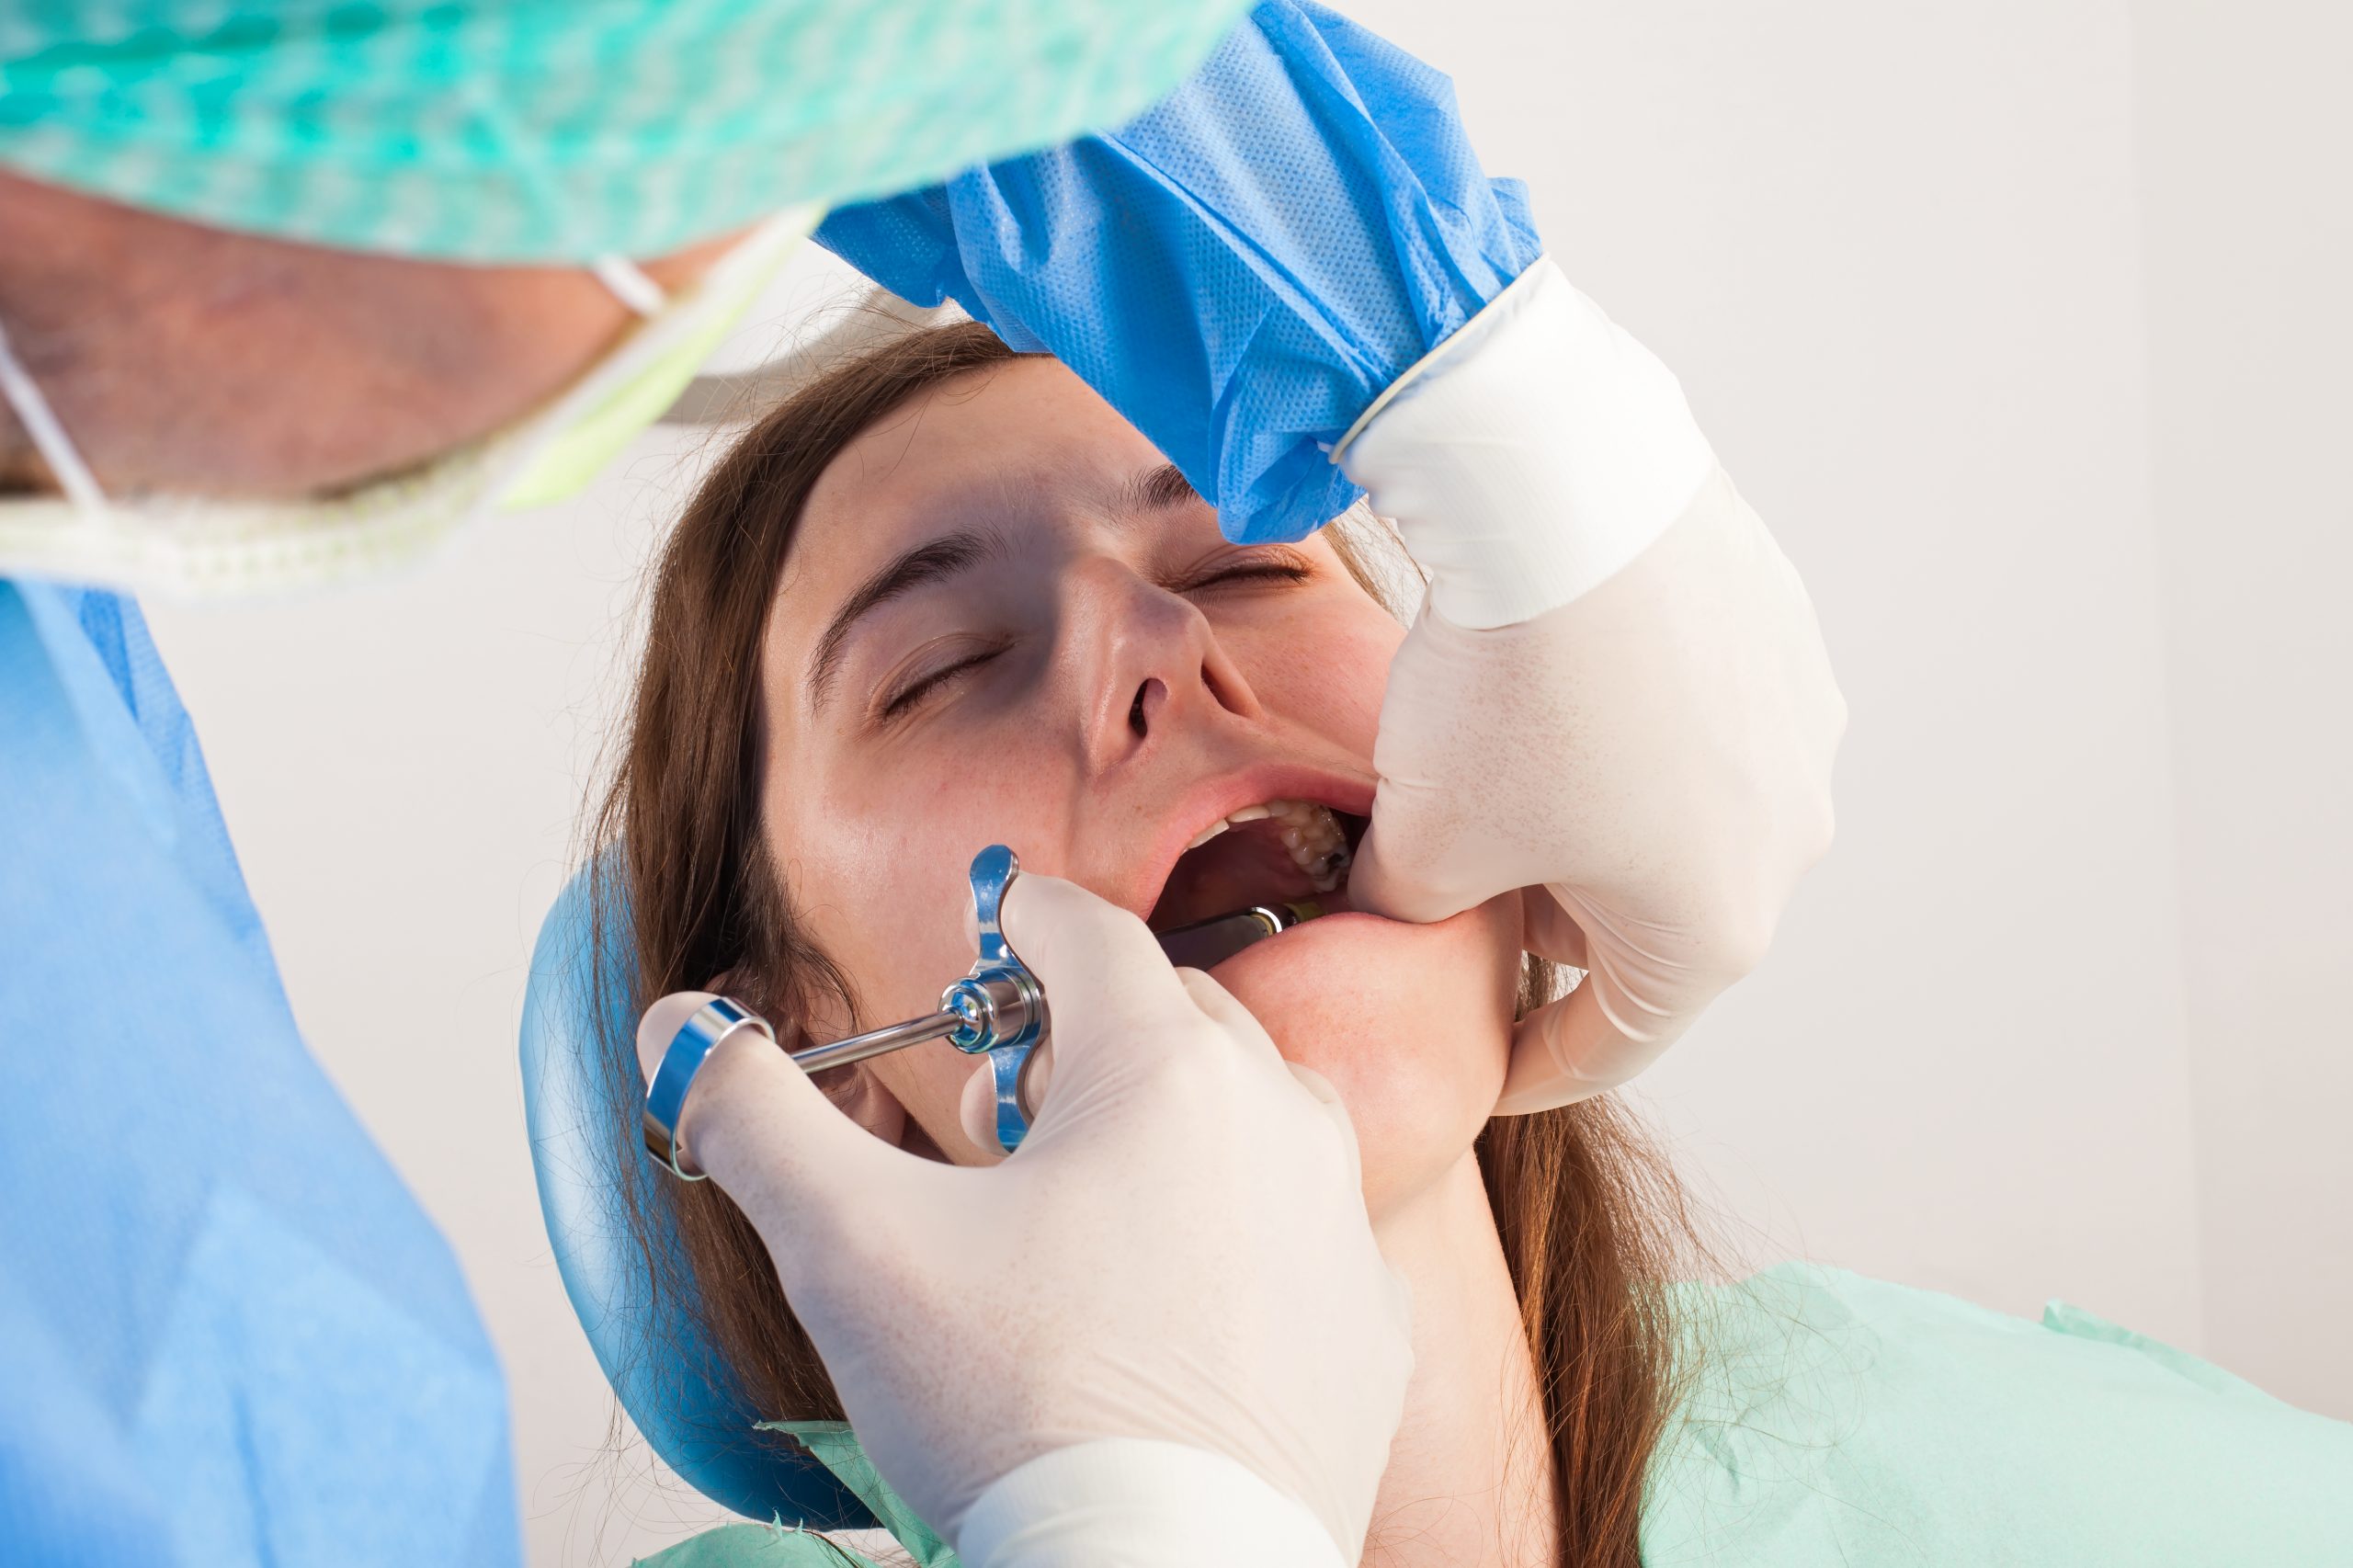
Woman receiving dental procedure.

Oral and maxillofacial surgeons (OMS) should take careful note of all allergies reported by patients, including those which are food-related. In this case study, a patient who reported an allergy to cherries develops cognitive deficits as a result of a severe allergic reaction to an ingredient in the topical anesthetic used by the OMS, which was the same allergen found in cherries. Later, the patient accuses the OMS of negligence.

Key Concepts

  • Office protocols to decrease the incidence of preventable errors
  • Disagreement between opposing litigation experts
  • Evaluating all aspects of a patient’s medical history

Background Facts

B, a 37-year-old woman, was referred to a local oral and maxillofacial surgeon, Dr. P, for the extraction of a fractured upper first molar. In the waiting room, B completed a medical and surgical history form, noting only a C-section delivery and an allergy to maraschino cherries. In responding to questioning about the reported allergy, B explained that, twice, she broke out with hives and generalized itching – with the second event being worse than the first after eating a cherry that was placed into her usual, go-to drink, an Old Fashioned.  

Dr. P entered the treatment operatory where B was seated, and explained that he would use a local anesthesia injection to numb the area, and then extract the broken tooth. Dr. P anticipated it would be a quick and straightforward procedure. After discussing risks, alternatives, and benefits, Y agreed to go forward.

Dr. P placed a cotton-tip swab of watermelon-flavored topical anesthesia into the mucobuccal fold, and left it in place for close to 2 minutes, before removing it and injecting a short-acting local anesthetic at the same location. Dr. P told B that he would give the anesthetic a few minutes to take effect, while he looked in on another patient, before treating her. The dental assistant began to set up the surgical tray, while making small talk with B, with her back to B. When the assistant noticed that B had stopped speaking with her, she turned to look at B and saw her face and neck were turning red, so she asked B how she was doing. B responded that she was not feeling well, sensing swelling in the back of her mouth and difficulty breathing.

The assistant immediately went to the adjacent treatment room where Dr. P was speaking with another patient. She did not want to interrupt the conversation, fearing that explaining her concerns would alarm that patient and cause Dr. P to be upset with her, she waited until the conversation ended before telling Dr. P that he needed to come to see B. Dr. P found B to be “barely conscious” struggling to breathe. He instructed the assistant to call 911, as he placed the nasal hood from the N2O/O2 setup over B’s nose, but the system had not yet been turned on for the day so no oxygen flowed until Dr. P was able to manipulate the valve to allow oxygen to flow. But B continued not to breathe, so Dr. P adjusted the dental chair to a supine position and manipulated B’s head to try to open the airway, but her chest still did not rise.

Dr. P began mouth-to-mouth resuscitation, with little apparent effect, until paramedics arrived and intubated B, thereby allowing oxygen into her lungs. Based upon communications with hospital personnel, epinephrine and corticosteroids were administered before transport to that hospital. B survived, but she claimed distinct cognitive deficits, later confirmed by a neurologist, which greatly impacted various facets of her life, including her occupation. The neurologist attributed those deficits to a transient oxygen deficit.

With the aid of her family members, B sought and retained an attorney to explore her options. The attorney gathered the records of Dr. P (including the documentation that accompanied the topical anesthetic agent) – the ambulance team, the hospital, and the neurologist – and passed those on to oral surgery and medical reviewers.  

The potential oral surgery expert learned that the topical anesthetic contained red dye #40, which is also found in maraschino cherries, and which is known to act as an allergen in certain people. The expert opined that Dr. P had been negligent in failing to adequately explore the patient’s reported allergy in the context of using a topical anesthetic which also happened to be red. When the attorney inquired of the expert whether such an ask of Dr. P was beyond the limits of reasonable foreseeability to constitute a violation of the standard of care, the expert responded that allergies can have such a significant and detrimental effect that no reported allergy should go without at least a reasonable investigation, especially when the only treatment at issue is clearly non-emergent. The expert was also of the opinion that Dr. P had failed to establish a proper office protocol to encourage his staff to interrupt anything if a patient’s immediate health might be at stake. Finally, the expert criticized Dr. P for leaving the patient unattended – except for a dental assistant whose primary duty at the time was to prepare for a procedure rather than to observe the patient after delivering the topical and local anesthetics.

The medical expert stated full agreement with the neurologist as to the cause of B’s cognitive deficits, and further attributed the transient oxygen deficit to the allergic reaction B experienced and to the delay in addressing it.

Finally, the attorney consulted with an occupational expert who personally evaluated B, interviewed her work supervisor, and looked at her relevant medical records. This expert opined that B no longer had the cognition required for her prior and still current position, and that, without a kind and understanding set of supervisors, B would not be able to maintain her job. However, she would not be able to advance to the extent that her prior work reviews anticipated for her, thereby depriving her of a substantial amount of income over her projected work life.

A suit was filed against Dr. P and his practice. Defense counsel was assigned by Dr. P’s malpractice carrier to defend Dr. P. After initial reviews of documents and interviewing Dr. P, they obtained the reviews of similar types of experts as had become involved on behalf of B. The oral surgery expert was generally in agreement with B’s oral surgery expert, except that she disagreed with it being a standard of care violation to leave the treatment room while local anesthesia was taking effect, saying, “that’s what just about everyone does”. The medical and occupational experts retained by defense counsel concluded almost exactly as did their counterparts.

Dr. P had been personally devastated by these events since they took place and did not want to fight B on the legal front. He encouraged his attorneys to do whatever they could to resolve the case without putting B and him through a courtroom battle. They did just that, and because a resolution came so early in the litigation, before B’s legal team had spent large amounts of money, an amount of settlement money that all involved thought to be fair and reasonable was agreed upon.

Takeaways

Addressing the final legal issue above first, the OMS’s personal input is an important factor in how he wishes to proceed in litigation. The OMS will have the option of either (1) defending his actions before a jury at trial, or (2) electing to consent to settle the lawsuit, thereby giving his insurance company the ability to determine whether early resolution of the lawsuit via settlement in lieu of proceeding to trial is the better option. Another factor sometimes considered is that of sympathy. While judges will generally instruct jurors that they are to exclude sympathy from their deliberations and verdicts, the human mind of those jurors might well be unable to make that exclusion, even unknowingly, as hard as they might try to do so.

Considering the major point of expert criticism against Dr. P, that of investigating all reported allergies, a larger tent within which to view this is that it is the obligation of oral surgeons to appropriately explore all aspects of the patient’s stated medical history to the point that the oral surgeon has a clear understanding that the planned treatment will be able to be performed safely, in all respects. Sometimes that exploration involves the oral surgeon becoming (re)familiar with the conditions presented. Sometimes it involves a phone call to a medical colleague or two to discuss the patient’s issues and potential fallout, and sometimes it means referring a patient to a physician, whether it’s their own established practitioner or one of the oral surgeon’s choosing. Whichever way an oral surgeon elects to assure patient safety, the critical end point is that patient safety must be assured.

This case demonstrates a number of circumstances that led to delays in the treatment of B, once the emergency came about. One of those which was addressed by B’s expert was that of failing to establish an office protocol such that a staff member can quickly and comfortably alert the oral surgeon to a problem that requires immediate attention. An approach – but by no means the only approach – to enable the communication of a serious concern without disturbing other patients is to set up a code word to be used between dentists and staff that indicates the need for prompt attention. We suggest using a word not commonly used in everyday interactions, such as “Saskatchewan” or “marmalade” (or any other term agreed upon), which is never spoken in the office except in emergencies. A second issue raised by B’s expert was the immediate unavailability of oxygen, here due to the valve not having been opened before patients started to be seen that day. Oxygen is an important emergency drug, so it is more than appropriate for it to be ready to be used with virtually no notice. The same approach might be employed for other drugs and/or equipment that play a crucial role in emergency care.

Finally, we note the disagreement between experts regarding the propriety of an oral surgeon leaving the treatment room while waiting for local anesthesia to take effect before starting the procedure. Disagreements among experts are the norm, rather than the exception, so matters of judgment should be exercised with due thought, weighing all considerations, and having a willingness and ability to defend the choice – not based upon “this is what I always do,” but instead, “this is why I do that.” The former carries little jury weight, while the latter sends the message of professionalism.

			WP_Query Object
(
    [query] => Array
        (
            [post_type] => post
            [showposts] => 3
            [post__not_in] => Array
                (
                    [0] => 6934
                )

            [post_status] => publish
            [has_password] => 
            [cat] => 1365
        )

    [query_vars] => Array
        (
            [post_type] => post
            [showposts] => 3
            [post__not_in] => Array
                (
                    [0] => 6934
                )

            [post_status] => publish
            [has_password] => 
            [cat] => 1365
            [error] => 
            [m] => 
            [p] => 0
            [post_parent] => 
            [subpost] => 
            [subpost_id] => 
            [attachment] => 
            [attachment_id] => 0
            [name] => 
            [pagename] => 
            [page_id] => 0
            [second] => 
            [minute] => 
            [hour] => 
            [day] => 0
            [monthnum] => 0
            [year] => 0
            [w] => 0
            [category_name] => risk-tips
            [tag] => 
            [tag_id] => 
            [author] => 
            [author_name] => 
            [feed] => 
            [tb] => 
            [paged] => 0
            [meta_key] => 
            [meta_value] => 
            [preview] => 
            [s] => 
            [sentence] => 
            [title] => 
            [fields] => all
            [menu_order] => 
            [embed] => 
            [category__in] => Array
                (
                )

            [category__not_in] => Array
                (
                )

            [category__and] => Array
                (
                )

            [post__in] => Array
                (
                )

            [post_name__in] => Array
                (
                )

            [tag__in] => Array
                (
                )

            [tag__not_in] => Array
                (
                )

            [tag__and] => Array
                (
                )

            [tag_slug__in] => Array
                (
                )

            [tag_slug__and] => Array
                (
                )

            [post_parent__in] => Array
                (
                )

            [post_parent__not_in] => Array
                (
                )

            [author__in] => Array
                (
                )

            [author__not_in] => Array
                (
                )

            [search_columns] => Array
                (
                )

            [ignore_sticky_posts] => 
            [suppress_filters] => 
            [cache_results] => 1
            [update_post_term_cache] => 1
            [update_menu_item_cache] => 
            [lazy_load_term_meta] => 1
            [update_post_meta_cache] => 1
            [posts_per_page] => 3
            [nopaging] => 
            [comments_per_page] => 50
            [no_found_rows] => 
            [order] => DESC
        )

    [tax_query] => WP_Tax_Query Object
        (
            [queries] => Array
                (
                    [0] => Array
                        (
                            [taxonomy] => category
                            [terms] => Array
                                (
                                    [0] => 1365
                                )

                            [field] => term_id
                            [operator] => IN
                            [include_children] => 1
                        )

                )

            [relation] => AND
            [table_aliases:protected] => Array
                (
                    [0] => wp_4_term_relationships
                )

            [queried_terms] => Array
                (
                    [category] => Array
                        (
                            [terms] => Array
                                (
                                    [0] => 1365
                                )

                            [field] => term_id
                        )

                )

            [primary_table] => wp_4_posts
            [primary_id_column] => ID
        )

    [meta_query] => WP_Meta_Query Object
        (
            [queries] => Array
                (
                )

            [relation] => 
            [meta_table] => 
            [meta_id_column] => 
            [primary_table] => 
            [primary_id_column] => 
            [table_aliases:protected] => Array
                (
                )

            [clauses:protected] => Array
                (
                )

            [has_or_relation:protected] => 
        )

    [date_query] => 
    [request] => SELECT SQL_CALC_FOUND_ROWS  wp_4_posts.ID
					 FROM wp_4_posts  LEFT JOIN wp_4_term_relationships ON (wp_4_posts.ID = wp_4_term_relationships.object_id)
					 WHERE 1=1  AND wp_4_posts.ID NOT IN (6934) AND ( 
  wp_4_term_relationships.term_taxonomy_id IN (11)
) AND wp_4_posts.post_password = '' AND wp_4_posts.post_type = 'post' AND ((wp_4_posts.post_status = 'publish'))
					 GROUP BY wp_4_posts.ID
					 ORDER BY wp_4_posts.post_date DESC
					 LIMIT 0, 3
    [posts] => Array
        (
            [0] => WP_Post Object
                (
                    [ID] => 8119
                    [post_author] => 180159417
                    [post_date] => 2026-10-13 15:18:51
                    [post_date_gmt] => 2026-10-13 19:18:51
                    [post_content] => 


When patients seek a second opinion after an unexpected outcome, even measured criticism from another provider can fuel doubt, escalate into “jousting,” and lead to a malpractice lawsuit. This case study demonstrates how clear documentation, realistic expectation-setting, and a strong informed consent process can help OMS manage malpractice risk.

Key concepts          

  • How "jousting" can stimulate the initiation of malpractice lawsuits
  • Risks associated with setting unrealistic treatment expectations
  • Documentation and defending care decisions

Background facts

Dr. Y was one of several oral and maxillofacial surgeons practicing in and around a well-populated suburban community. Although most of her practice involved dentoalveolar treatments and implant placement, she maintained privileges at a local hospital for the rare need to hospitalize her patients. A requirement for maintaining privileges was taking emergency call one weekend every three months, as there were no residents on staff, but emergencies requiring coming to the hospital were few and far between. Dr. Y had done little in the way of trauma surgery in the 14 years since the conclusion of residency.

A multi-vehicle, high-speed accident occurred on a Sunday evening, some 20 miles from the hospital. The most severely injured were taken to a trauma center, but space there quickly filled up, leaving less seriously injured patients to be taken to smaller hospitals, including where Dr. Y was on staff. The only injury found after initial evaluation of T, a 28-year-old bus passenger, was a zygomatic arch fracture on her right side, which apparently occurred when her face hit the back of the seat in front of her. When Dr. Y, who had been called to attend to this patient, examined T, she found significant swelling associated with the right midface that correlated with radiographic and clinical evaluations. Dr. Y noted and documented that there appeared to be a facial nerve deficiency associated with the zygomatic branch of cranial nerve VII.

By way of a face-to-face discussion, Dr. Y explained that she would approach the depressed fracture through an intraoral incision to avoid facial scarring and then tunnel upward with a heavy zygomatic elevator to “pop it back into place.” To allow the bone to heal afterward, Dr. Y would place an external device over the arch so that T would not roll onto it while asleep or otherwise inadvertently put any inward-directed pressure on the area. Dr. Y explained that she “expected everything to be back to normal within a couple of months.” After agreeing and signing a standard generic hospital “consent for surgery” form, T was taken to the OR where, under general anesthesia, Dr. Y uneventfully performed exactly what she had described to T. T was discharged home the following day, with instructions to see Dr. Y in her office the next week.

There were weekly office visits for the first month, with two visits the second month and a final appointment at the three-month mark. The fracture was stable, all swelling had resolved, and T was functioning fully normally, with one exception: T never regained the ability to close her right eye. Dr. Y acknowledged the problem and told T that the nerve's function might not ever return, leaving T with the same condition permanently. T responded with, “But you told me everything would be back to normal by now.” Dr. Y explained that, most often, traumatically induced nerve injuries like this do normalize, “although nothing is 100%.” 

T was dissatisfied with both the result and Dr. Y's explanation, which she had not fully set out from the start, so she visited a facial plastic surgeon for a second opinion. That surgeon concurred with Dr. Y's assessment of a low likelihood of nerve recovery, but also commented that, had he been the one treating the fracture, he might have chosen a different approach — without providing the details of that difference — and the nerve might have recovered. T asked the plastic surgeon to put that opinion into a written narrative, which he did.

Legal action

When T saw an attorney who advertised regularly handling medical malpractice cases, she brought the plastic surgeon's note with her. She was distressed by the aesthetic impact of her inability to close her eye and the need for her to use eye drops daily. The attorney concluded that the surgeon's note adequately presented a viable case against Dr. Y, so he proceeded on T's behalf by filing a malpractice lawsuit against Dr. Y. The papers claimed negligence in the type of surgical procedure chosen and performed, and lack of informed consent.

Based upon state-specific rules, the attorneys assigned to Dr. Y by her malpractice carrier were not able to file a motion to dismiss the case until a shortly later stage of the case. At the appropriate time, they did submit such a filing, in which they argued, in essence, that the nerve was already injured before Dr. Y intervened; that the opinion of T's expert included the words “might have” with regard to the two main points of claimed negligence and injury (namely the surgical approach and nerve function); that there are multiple accepted surgical approaches to repair a depressed zygomatic arch fracture, with the choice being wholly within the judgment of the treating surgeon, at the time of surgery rather than looking back on it; and that no reasonable person would have refused surgery to repair a severely fractured facial bone, even if return to normal nerve function would never occur. An oral and maxillofacial surgery expert retained by Dr. Y's attorneys echoed these concepts in the court papers.

The attorney for the plaintiff, T, obtained a further document from the plastic surgeon with whom T had consulted. The surgeon was no more definitive in the second document than he had been in the first. In deciding the motion, the judge explained that the burden of proof, “more likely than not,” must be met by a plaintiff as to each element of the case, with words such as “might have” failing to meet that burden. Furthermore, based upon local doctrines that were applicable here, the “reasonable person” standard regarding informed consent would carry the day, particularly because this was a true emergency situation. The case against Dr. Y was dismissed by the court in its entirety.

Takeaways

Much like already-in-progress procedures taken over from other providers, trauma surgery presents a set of unknowns which, in some sense, the oral surgeon who takes over and completes the surgery “buys” whatever existed as of the start of the second intervention. As this case demonstrates, that does not necessarily equate to liability for what happened previously, but it also does not necessarily mean that plaintiffs and their attorneys will not try to assert and prove such a claim. These types of situations are, for better or worse, part of oral surgery practice, so oral surgeons should be aware of that. Perhaps the best way to set up what might later be needed to defend such allegations is what is greatly helpful in the defense of many malpractice claims — timely, accurate, and complete documentation. That is as good a counter as is possible against an often-used approach by plaintiffs' lawyers that “if it wasn't written, it didn't really happen.” 

Exceptions to the need to obtain informed consent vary between the states, sometimes significantly, so it is up to oral surgeons to know, at least basically, what local rules require. It is far from uncommon for exceptions in this regard regarding emergencies to exist, but as with much in the law, interpretations come into play. One person's definition of an emergency can readily differ from that of another person, so those components of the competing arguments are what will likely lead to a judge's ultimate determination. Oral surgeons should not necessarily count on exceptions to statutory concepts like informed consent, so whenever possible, it is most prudent to stick to the true “letter of the law.” 

In this case, Dr. Y set up an anticipation of end-of-day normalcy in her explanation to T of what to expect. With the benefit of hindsight, an argument can readily be made that a less definitive and more open-ended “prediction” of future nerve function would have been safer from a risk-protective standpoint. As the (trite) saying goes, words matter, and that is particularly true when discussing all aspects of risks, benefits, and alternatives. The plastic surgeon's words changed the entire trajectory of the litigation, and the words of Dr. Y could just as easily have done the same, but in the opposite direction. 

The comments by the plastic surgeon that were critical of Dr. Y's surgical approach are referred to as “jousting,” which is a frequent inspiration for patients to act on taking steps to sue the doctor(s) criticized. Jousters never stood in the shoes of the original treater at the time of treatment, so they do not and cannot know the full story, yet their statements are often potent. Furthermore, it is far from uncommon for jousters to later testify against the sued provider, on behalf of the plaintiff-patient.  Of course, they are then subject to cross-examination, when the weaknesses of an after-the-fact assessment will be raised for a jury to hear and consider. The back-and-forth of trial.

(For readers who might be wondering about whether T was able to be compensated by way of a lawsuit regarding the highway accident, complex jurisdictional issues prevented combining that case with the malpractice suit against Dr. Y. So, we have intentionally separated the two actions here, focusing only upon oral surgery treatment considerations.)

Summary of takeaways

  • Timely, accurate notes can help show what injuries were already present, what decisions were made, and why treatment was appropriate.
  • Rules vary by state, so oral surgeons should follow the clearest informed consent process possible whenever circumstances allow.
  • Avoid definitive promises, document risks clearly, and be aware that second-opinion “jousting” can influence a patient’s decision to sue.

[post_title] => A Second Opinion After OMS Trauma Care Leads to a Malpractice Lawsuit [post_excerpt] => [post_status] => publish [comment_status] => open [ping_status] => open [post_password] => [post_name] => a-second-opinion-after-oms-trauma-care-leads-to-a-malpractice-lawsuit [to_ping] => [pinged] => [post_modified] => 2026-10-30 15:04:26 [post_modified_gmt] => 2026-10-30 19:04:26 [post_content_filtered] => [post_parent] => 0 [guid] => https://oms.medprodental.com/?p=8119 [menu_order] => 0 [post_type] => post [post_mime_type] => [comment_count] => 0 [filter] => raw ) [1] => WP_Post Object ( [ID] => 8110 [post_author] => 180159417 [post_date] => 2026-10-08 02:23:12 [post_date_gmt] => 2026-10-08 06:23:12 [post_content] =>

In this real-life case study, OMS will learn how a simple communication breakdown between offices resulted in the extraction of the wrong tooth. Learn why accurate referrals, staff protocols, and pre-treatment verification are critical to managing risk.

Key concepts        

  • Referral communication breakdowns and risk management
  • How vicarious liability applies to staff errors
  • Why “time out” protocols help prevent treatment errors

Background facts

Dr. Q is a restorative dentist in a suburban community. While she used to practice the full spectrum of general dentistry, over the last few years she has focused exclusively on restorative cases, referring patients who need all other areas of dental care to other providers. P was a 37-year-old man who had been a patient of Dr. Q's for nearly a decade.

During a weekend soccer game, P "headed" the ball to a teammate, and it struck the right mid-face, somewhat lower than the forehead area he intended. There was some lingering pain on P's face for the remainder of the game, but he did not think much of it. At dinner that evening, he found himself with shock-like discomfort emanating from his upper right teeth, although he could not pinpoint a specific tooth as the source. When the situation did not resolve after several days, he presented to see Dr. Q.

When Dr. Q examined the quadrant, she noted tooth #2 to have a large 3-surface amalgam in place, but she could not elicit any abnormal responses through percussion or palpation, nor could she find anything unusual on radiograph or with an explorer. On the other hand, #3, which was a virgin tooth, was tender to all modalities, and it clinically exhibited a probable vertical MB root fracture beginning at the furcation and extending apically. Dr. Q concluded the tooth to be non-restorable, so she suggested its extraction — by an oral surgeon — with an implant and crown for replacement. Dr. Q entered her electronic note, explaining the situation regarding both teeth #2 and 3, and handing P a handwritten referral card, asking Dr. E, an oral and maxillofacial surgeon, to extract #3 and place a bone graft so that she (Dr. Q) could later place an implant and restore it. 

Dr. Q's front desk staff member called Dr. E's office to say that "we're sending over a patient, P, for an extraction.” Dr. E replied, "OK.” Either before or during the short drive to see Dr. E, P misplaced or lost the referral card. All he knew was that an upper right tooth needed to come out. P "frantically" called Dr. Q's office to ask that a fax be sent to Dr. E with the information as to the tooth to be extracted. Dr. Q's office manager quickly scanned the newly written note from just a few minutes prior, focused solely on the first portion of the chart entry, which stated that tooth #2 had a "large, old MOD amalgam,” presumed that was the tooth in need of treatment, and faxed "please ext tooth #2,” unsigned, on Dr. Q's letterhead. After taking a periapical radiograph of teeth #1-3 (distal half only of #3 captured), obtaining P's signature on a consent form for "extraction upper right molar,” and giving local anesthesia, Dr. E did exactly what the letter from Dr. Q asked him to do. A post-extraction periapical more clearly and completely showed tooth #3, adjacent to the new extraction site, with an apparent vertical MB root fracture.

Dr. E immediately called Dr. Q after realizing his error, and the two concluded that he ought to explain the event to P and then extract tooth #3. Dr. E asked P to initial the newly modified consent form, which added the letter "s" to "molar." P complied. Drs. Q and E would work together to provide 2 implants with 2 crowns, all at no cost. Those treatments later went forward uneventfully, with P being able to function without limitation, although he always worried about his dental future. It is worth noting that P had been in family therapy — for totally unrelated reasons — prior to these events, but he began to talk extensively with his therapist about his upset over the dentistry, with all of that recorded in the therapy chart.

Legal action

P was clearly aware that he would have no out-of-pocket expenses due to the wrongly extracted tooth. In fact, whereas he would have paid for the 1 implant and 1 crown for tooth #3 had there been no error, he no longer had to, based upon the goodwill gestures of both doctors. But it was no longer about money needed for the dentistry: he wanted to be compensated for the stress of the entire situation. P was unable to find an attorney willing to take his case against Drs. Q and E, so he decided to file a malpractice lawsuit in City Court, which, in his jurisdiction, was a level higher than Small Claims and a level lower than the general trial court, and which readily enabled him to handle the case on his own, as a pro se litigant. The City Court's "DIY" web page set out the procedures to abide by, the most important of which was a reasonable degree of relaxation of rules of evidence. For example, copies of medical and dental records could be introduced without the author being present to testify about and certify them. A judge would preside and would render a verdict.

At the trial, both of the defendant doctors were represented by attorneys assigned to them by their malpractice insurers, as malpractice policies generally provide, regardless of the level of the court. P argued, essentially, that he was an unwitting victim, with no role in any wrongdoing, but with both doctors being careless — either personally or through their employees — so as to directly cause the wrong tooth to be extracted. The impacts of that error became part of the case evidence when the judge allowed the detailed chart entries of P's therapist, which described his emotional distress, to satisfy his claim for damages.

A major stance taken by Dr. Q's counsel was that she had done everything properly, and it was solely because P was careless in losing the referral card which led to the office manager's hurried documentation mistake, but Dr. Q had performed no dentistry in a negligent fashion. Dr. E's counsel took the position that P agreed to have both teeth removed, as demonstrated by his signature and initials on a form which gave Dr. E permission to extract upper right "molars" (plural). But when the judge questioned P about the specific events involving the consent form modification, and had that confirmed by Dr. E, she disallowed the consent form in its entirety, ruling that informed consent is a pre-treatment process, which must be voluntary to be valid, and this document, in the form presented, represented neither pre-treatment nor voluntary (because by the time P initialed, he no longer had any choices).

In the end, the judge held both doctors liable and awarded P a modest sum for the emotional distress he suffered, but nothing for actual costs, as there were none. The judge said that, even though Dr. Q did not herself, but through an employee, make a transcription error, the concept of vicarious liability meant that actions taken by Dr. Q's employee, as part of employment, were as though the erroneous actions were committed by Dr. Q. The judge then turned to Dr. E and suggested that his mid-procedure attempt to make it seem as though this had all been planned in advance was misleading to the court, at best. For this reason, she levied the majority of the responsibility against Dr. E.

Takeaways

By way of the concept known as vicarious liability, a dentist (and/or a practice entity) is responsible for the acts of those who work under the dentist's supervision, whether that supervision is direct or simply implied. Therefore, even though Dr. Q did not perform any negligent act herself, it is as though she did. It is important for practitioners to be aware of this in the course of overseeing the actions of all of their staff members that are involved with patient contact to any degree. And it is critical that they be aware of which duties may be properly delegated and which must not. Here, had the office manager who wrote the replacement referral shown it to Dr. Q for a final sign-off, the ultimate dental error would likely have never happened. As an alternative, Dr. Q could have established office policy that would have avoided the mistake, namely making and keeping a chart copy of the referral card initially given to P. If that had been done, the office manager would have simply been able to fax a copy of what Dr. Q actually created, eliminating any chance of interpersonal miscommunication altogether. 

Informed consent is a process, often and hopefully memorialized with a signed writing, that gives a patient decision-making authority before the start of a procedure, once made aware of risks, benefits, and alternatives: it is not valid after a procedure or during the procedure, by which time there are no longer any true choices to be made. Engaging in the process any time other than prior to its start is a mere pretext, which, at least in this judge's courtroom, was legally invalid. The viewing of Dr. E's actions in this regard as misleading is not necessarily anything but the assessment of one person, who happened to be the judge, but it might well also be reflective of how jurors might view it and act. This clearly demonstrates why every part of a patient record should be created, not only truthfully, but with an eye toward who might someday read and evaluate it.

Wrong-site treatment, especially surgery, has become an increasingly frequent event among dentists in all practice areas. The "time out" concept — to assure proper patient, proper site, and patient-chart match - before a procedure starts, as our medical colleagues do well and fairly consistently, cannot be overstated as a critically important step. In doing so, all members of the team should be encouraged to alert the treating doctor, in a way that does not alarm the patient, any time something seems amiss, with no repercussions for a "false alarm.”

Finally, given dentistry's multiple and sometimes confusing tooth numbering systems, identifying a tooth by its name, rather than by a number, can provide true simplicity and better accuracy. It would be difficult to argue against the clarity of saying "upper right first molar" as compared with Universal #3 or Palmer upper right 6 or FDI 16. It's easy to clear up those muddy waters every time. 

Summary of takeaways

  • OMS may be held responsible for staff actions, so referral information should be clearly documented, preserved in the chart, and reviewed before it is sent to another provider.
  • Informed consent must be obtained before treatment begins. Attempts to modify consent forms during or after a procedure will weaken credibility and likely render defensibility unsuccessful.
  • Wrong-site treatment can nearly always be prevented with a consistent “time out” process and clear tooth identification using plain-language names instead of numbers alone.
[post_title] => Referral Miscommunication Leads to Wrong-Tooth Extraction  [post_excerpt] => [post_status] => publish [comment_status] => open [ping_status] => open [post_password] => [post_name] => referral-miscommunication-leads-to-wrong-tooth-extraction [to_ping] => [pinged] => [post_modified] => 2026-10-20 03:13:29 [post_modified_gmt] => 2026-10-20 07:13:29 [post_content_filtered] => [post_parent] => 0 [guid] => https://oms.medprodental.com/?p=8110 [menu_order] => 0 [post_type] => post [post_mime_type] => [comment_count] => 0 [filter] => raw ) [2] => WP_Post Object ( [ID] => 8086 [post_author] => 180159417 [post_date] => 2026-09-06 22:04:12 [post_date_gmt] => 2026-09-07 02:04:12 [post_content] =>

This real-life OMS case study illustrates how patient anatomy, clinical judgment, and external pressures can turn a complex treatment plan into a malpractice claim. Learn why it’s critical to trust your professional judgment, recommend only viable treatment options, and prioritize patient safety when weighing surgical risks and alternatives.

Key concepts

  • All-on-4 procedure leads to serious complication
  • Trusting your clinical judgment
  • Risk management lessons for implant dentistry

Background facts

R was a 61-year-old generally healthy man who had worn maxillary full dentures for years, but was becoming increasingly dissatisfied with them, both functionally and esthetically. His lower arch posed no problems for him: other than a 3-unit fixed bridge on the right and a 4-unit bridge on the left, he had natural teeth in place. In the past, he was a nearly pack-a-day smoker, but he had since overcome that habit. He presented to a multispecialty dental office he had seen advertised locally, seeking to improve the condition of his maxilla.

He initially saw a prosthodontist, who evaluated the mouth and concluded that an implant-supported prosthesis would work well for R. Per office policy, the on-site oral surgeon would handle the implant aspect of treatment, with the patient then returning to the prosthodontist for the restoration. That same day, the OMS, Dr. G, met with R, ordered a CBCT study, reviewed it, and discussed the available options. Because of the paucity of maxillary bone — especially posteriorly — and "low-lying" maxillary sinus cavities, a traditional implant arrangement would not be possible. So, 2 options were available: (1) perform bilateral sinus lifts with bone grafting, allow for an adequate healing period, place 3 implants (potentially) on each side, and then restore the maxilla prosthetically after osseointegration; or (2) do an all-on-4 procedure using the pterygoid bones bilaterally for both posterior implants, place a provisional prosthetic appliance that same day, and later convert to a permanent prosthesis after integration.

The office management encouraged the most time-efficient case completions possible. With that in mind, Dr. G and the prosthodontist discussed the available options, with Dr. G expressing some concern about the radiographically appearing rather thin pterygoids, particularly on the right side. However, the prosthodontist did not want to wait for the entire sinus lift process to play out, and encouraged the OMS to do the all-on-4 approach, despite her stated concerns. Dr. G (reluctantly) agreed, and so did R, after they had a full discussion about the most common risks, benefits, and options, with R signing a consent form.

On the day of treatment, R took the oral sedative prescribed for him by Dr. G, just before leaving home. Dr. G injected local anesthetic solution buccally and palatally across the entire upper jaw. Because she is left-handed, Dr. G began with her preferred side, the left, because access was easier. Referring to the CBCT images, she uneventfully placed 2 implants on the left side, 1 at the approximate site where tooth #11 had been, and 1 angled into the pterygoid: both were clinically stable. She then turned to the right side to place 2 implants before the prosthodontist placed the ready provisional. The implant near the prior site of the upper right canine was smoothly placed. In performing the right pterygoid osteotomy, Dr. G's concern came to fruition, as the bur, which had initially been met with typical bony resistance, suddenly fell into a void, which she presumed to be the pterygopalatine fossa. When she backed out the handpiece, bright red, pulsating blood heavily flowed into the mouth, clouding the entire field.

Her initial approach was to pack the site with gauze strips, which did slow the flow, but the gauze quickly filled with blood and continued to do so despite repeated packing. Dr. G believed that she had pierced into (a branch of) the right maxillary artery. With her being unable to gain hemostatic control, and being in an outpatient setting with an awake patient, she attempted to gain access to the source of the bleed by entering the maxillary sinus through a Caldwell-Luc approach, and then cutting a window through the posterior sinus wall to enter the fossa. But doing so only provided a second outlet of significant bleeding, leading her to conclude that ligating the artery required in-hospital care by a head and neck surgeon. R was transported by ambulance to a nearby medical center, with Dr. G accompanying him to try to maintain site pressure as they travelled. R was emergently taken to the OR, where he was induced and intubated, and where an ENT surgeon unsuccessfully attempted access to the torn vessel endoscopically, ultimately ligating the vessel some 2 hours later by way of a preauricular approach infratemporally. R remained in hospital for a week, and missed work for more than a month, left with a scar and always feeling limitations to his usual exercise routine.

Legal action

R's newly retained attorney obtained all of the relevant dental and medical records, and sent them on to an academic-based OMS for review. That expert passed on his conclusions to the attorney who hired him: that Dr. G succumbed to external pressures and performed a procedure that she knew was concerning and risky, given the specific anatomy presented, and that the preferred set of procedures for this patient would have begun with the sinus lift and graft approach. The attorney also contacted the treating ENT, who was willing to provide his opinion that the bleed and the resultant surgery and after-effects were due to an ill-conceived surgical treatment plan by Dr. G.

Dr. G contacted her malpractice carrier when she provided records to R's attorney, and again when she was served with papers that initiated the lawsuit against her. She had personally been deeply upset by the events, now some months ago, and she told her assigned attorney that she was eager to put this behind her, partly for the personal impact but also because she realized that she had not exercised her best judgment.

Settlement moves began quickly, with an agreement reached before discovery even started. In addition to money, which covered medical costs, physical and emotional distress, and lost income, R made a somewhat unusual request: that Dr. G write an apology and explanation to him, which he felt that he needed to close the chapter. Despite her attorney advising Dr. G against doing so, explaining the potential impacts upon a Board complaint (which never happened) or hospital credentialing, she did as R had asked, because she, too, needed the closure.

Takeaways

Pressures are frequently placed on practitioners, including oral surgeons, from sources as diverse as patients, dental or medical colleagues, and practice supervisors and owners. The reasons for the responses to those pressures are equally diverse, from the need to maintain employment, to conflict aversion, to ego. In the end, though, all that really matters on the legal side of practice are adherence to standards of care and principles of ethics. Perhaps, a safe approach for practitioners to take is that if something simply does not feel right, stay away from it. While that might not always be practical, it can at least be an internal starting point, if not ultimately the end point.

It is the general rule, rather than the exception, that there are most often multiple options/alternatives to overcome dental and surgical problems. Principles of informed consent dictate the requirement to advise patients of, among other things, available alternatives. But that does not mean every alternative, only the viable ones. And if an alternative is not viable for any reason, whether because of patient anatomy, underlying patient medical conditions and social habits, or provider limitations (based upon ability or experience), that alternative falls out of the realm of informed consent. Here, the anatomy of R's right pterygoid and, perhaps (reading between the lines) her own limitations, Dr. G seemingly knew that an all-on-4 plan was not viable for R. Fighting her better judgment was a clear factor in the events and injuries.

All procedures carry risk. It is part and parcel of healthcare delivery, particularly when surgery is involved. Practitioners appropriately take specific risks into account when weighing the potential coming to fruition of those risks against the benefits of doing the procedure. There is no one-size-fits-all formula to use to come to a decision, but instead a subjective process that is individual to every surgeon, considering a host of factors. Many risks come to pass (in the form of injury) in the absence of any negligence, with that concept being a foundation for much of malpractice defense, but when injuries occur because of negligence, that often becomes the very basis for plaintiffs' cases against doctors.

Decisions about settlement versus trial are extremely case-specific, with the insurer, counsel, and all litigants playing significant roles. Practitioners who have "pure consent" policies are permitted, per policy language, to withhold consent to a settlement, in favor of going to trial. But in cases where practitioners do provide their consent to settle, that does not mean that the malpractice carrier must then settle the case, but simply that it may agree to a settlement. Think of it as a permission slip, but not a requirement slip.

Summary of takeaways

  • External pressures should never outweigh clinical judgment when determining the most appropriate treatment plan.
  • Not every treatment option is suitable for every patient — anatomy, provider experience, and overall risk must be carefully evaluated before proceeding.
  • When complications occur, treatment decisions that fall outside the standard of care can increase liability exposure and lead to malpractice claims.

[post_title] => All-on-4 Implant Procedure Leads to Malpractice Claim Against OMS [post_excerpt] => [post_status] => publish [comment_status] => open [ping_status] => open [post_password] => [post_name] => all-on-4-implant-procedure-leads-to-malpractice-claim-against-oms [to_ping] => [pinged] => [post_modified] => 2026-10-30 10:17:55 [post_modified_gmt] => 2026-10-30 14:17:55 [post_content_filtered] => [post_parent] => 0 [guid] => https://oms.medprodental.com/?p=8086 [menu_order] => 0 [post_type] => post [post_mime_type] => [comment_count] => 0 [filter] => raw ) ) [post_count] => 3 [current_post] => -1 [before_loop] => 1 [in_the_loop] => [post] => WP_Post Object ( [ID] => 8119 [post_author] => 180159417 [post_date] => 2026-10-13 15:18:51 [post_date_gmt] => 2026-10-13 19:18:51 [post_content] =>

When patients seek a second opinion after an unexpected outcome, even measured criticism from another provider can fuel doubt, escalate into “jousting,” and lead to a malpractice lawsuit. This case study demonstrates how clear documentation, realistic expectation-setting, and a strong informed consent process can help OMS manage malpractice risk.

Key concepts          

  • How "jousting" can stimulate the initiation of malpractice lawsuits
  • Risks associated with setting unrealistic treatment expectations
  • Documentation and defending care decisions

Background facts

Dr. Y was one of several oral and maxillofacial surgeons practicing in and around a well-populated suburban community. Although most of her practice involved dentoalveolar treatments and implant placement, she maintained privileges at a local hospital for the rare need to hospitalize her patients. A requirement for maintaining privileges was taking emergency call one weekend every three months, as there were no residents on staff, but emergencies requiring coming to the hospital were few and far between. Dr. Y had done little in the way of trauma surgery in the 14 years since the conclusion of residency.

A multi-vehicle, high-speed accident occurred on a Sunday evening, some 20 miles from the hospital. The most severely injured were taken to a trauma center, but space there quickly filled up, leaving less seriously injured patients to be taken to smaller hospitals, including where Dr. Y was on staff. The only injury found after initial evaluation of T, a 28-year-old bus passenger, was a zygomatic arch fracture on her right side, which apparently occurred when her face hit the back of the seat in front of her. When Dr. Y, who had been called to attend to this patient, examined T, she found significant swelling associated with the right midface that correlated with radiographic and clinical evaluations. Dr. Y noted and documented that there appeared to be a facial nerve deficiency associated with the zygomatic branch of cranial nerve VII.

By way of a face-to-face discussion, Dr. Y explained that she would approach the depressed fracture through an intraoral incision to avoid facial scarring and then tunnel upward with a heavy zygomatic elevator to “pop it back into place.” To allow the bone to heal afterward, Dr. Y would place an external device over the arch so that T would not roll onto it while asleep or otherwise inadvertently put any inward-directed pressure on the area. Dr. Y explained that she “expected everything to be back to normal within a couple of months.” After agreeing and signing a standard generic hospital “consent for surgery” form, T was taken to the OR where, under general anesthesia, Dr. Y uneventfully performed exactly what she had described to T. T was discharged home the following day, with instructions to see Dr. Y in her office the next week.

There were weekly office visits for the first month, with two visits the second month and a final appointment at the three-month mark. The fracture was stable, all swelling had resolved, and T was functioning fully normally, with one exception: T never regained the ability to close her right eye. Dr. Y acknowledged the problem and told T that the nerve's function might not ever return, leaving T with the same condition permanently. T responded with, “But you told me everything would be back to normal by now.” Dr. Y explained that, most often, traumatically induced nerve injuries like this do normalize, “although nothing is 100%.” 

T was dissatisfied with both the result and Dr. Y's explanation, which she had not fully set out from the start, so she visited a facial plastic surgeon for a second opinion. That surgeon concurred with Dr. Y's assessment of a low likelihood of nerve recovery, but also commented that, had he been the one treating the fracture, he might have chosen a different approach — without providing the details of that difference — and the nerve might have recovered. T asked the plastic surgeon to put that opinion into a written narrative, which he did.

Legal action

When T saw an attorney who advertised regularly handling medical malpractice cases, she brought the plastic surgeon's note with her. She was distressed by the aesthetic impact of her inability to close her eye and the need for her to use eye drops daily. The attorney concluded that the surgeon's note adequately presented a viable case against Dr. Y, so he proceeded on T's behalf by filing a malpractice lawsuit against Dr. Y. The papers claimed negligence in the type of surgical procedure chosen and performed, and lack of informed consent.

Based upon state-specific rules, the attorneys assigned to Dr. Y by her malpractice carrier were not able to file a motion to dismiss the case until a shortly later stage of the case. At the appropriate time, they did submit such a filing, in which they argued, in essence, that the nerve was already injured before Dr. Y intervened; that the opinion of T's expert included the words “might have” with regard to the two main points of claimed negligence and injury (namely the surgical approach and nerve function); that there are multiple accepted surgical approaches to repair a depressed zygomatic arch fracture, with the choice being wholly within the judgment of the treating surgeon, at the time of surgery rather than looking back on it; and that no reasonable person would have refused surgery to repair a severely fractured facial bone, even if return to normal nerve function would never occur. An oral and maxillofacial surgery expert retained by Dr. Y's attorneys echoed these concepts in the court papers.

The attorney for the plaintiff, T, obtained a further document from the plastic surgeon with whom T had consulted. The surgeon was no more definitive in the second document than he had been in the first. In deciding the motion, the judge explained that the burden of proof, “more likely than not,” must be met by a plaintiff as to each element of the case, with words such as “might have” failing to meet that burden. Furthermore, based upon local doctrines that were applicable here, the “reasonable person” standard regarding informed consent would carry the day, particularly because this was a true emergency situation. The case against Dr. Y was dismissed by the court in its entirety.

Takeaways

Much like already-in-progress procedures taken over from other providers, trauma surgery presents a set of unknowns which, in some sense, the oral surgeon who takes over and completes the surgery “buys” whatever existed as of the start of the second intervention. As this case demonstrates, that does not necessarily equate to liability for what happened previously, but it also does not necessarily mean that plaintiffs and their attorneys will not try to assert and prove such a claim. These types of situations are, for better or worse, part of oral surgery practice, so oral surgeons should be aware of that. Perhaps the best way to set up what might later be needed to defend such allegations is what is greatly helpful in the defense of many malpractice claims — timely, accurate, and complete documentation. That is as good a counter as is possible against an often-used approach by plaintiffs' lawyers that “if it wasn't written, it didn't really happen.” 

Exceptions to the need to obtain informed consent vary between the states, sometimes significantly, so it is up to oral surgeons to know, at least basically, what local rules require. It is far from uncommon for exceptions in this regard regarding emergencies to exist, but as with much in the law, interpretations come into play. One person's definition of an emergency can readily differ from that of another person, so those components of the competing arguments are what will likely lead to a judge's ultimate determination. Oral surgeons should not necessarily count on exceptions to statutory concepts like informed consent, so whenever possible, it is most prudent to stick to the true “letter of the law.” 

In this case, Dr. Y set up an anticipation of end-of-day normalcy in her explanation to T of what to expect. With the benefit of hindsight, an argument can readily be made that a less definitive and more open-ended “prediction” of future nerve function would have been safer from a risk-protective standpoint. As the (trite) saying goes, words matter, and that is particularly true when discussing all aspects of risks, benefits, and alternatives. The plastic surgeon's words changed the entire trajectory of the litigation, and the words of Dr. Y could just as easily have done the same, but in the opposite direction. 

The comments by the plastic surgeon that were critical of Dr. Y's surgical approach are referred to as “jousting,” which is a frequent inspiration for patients to act on taking steps to sue the doctor(s) criticized. Jousters never stood in the shoes of the original treater at the time of treatment, so they do not and cannot know the full story, yet their statements are often potent. Furthermore, it is far from uncommon for jousters to later testify against the sued provider, on behalf of the plaintiff-patient.  Of course, they are then subject to cross-examination, when the weaknesses of an after-the-fact assessment will be raised for a jury to hear and consider. The back-and-forth of trial.

(For readers who might be wondering about whether T was able to be compensated by way of a lawsuit regarding the highway accident, complex jurisdictional issues prevented combining that case with the malpractice suit against Dr. Y. So, we have intentionally separated the two actions here, focusing only upon oral surgery treatment considerations.)

Summary of takeaways

  • Timely, accurate notes can help show what injuries were already present, what decisions were made, and why treatment was appropriate.
  • Rules vary by state, so oral surgeons should follow the clearest informed consent process possible whenever circumstances allow.
  • Avoid definitive promises, document risks clearly, and be aware that second-opinion “jousting” can influence a patient’s decision to sue.

[post_title] => A Second Opinion After OMS Trauma Care Leads to a Malpractice Lawsuit [post_excerpt] => [post_status] => publish [comment_status] => open [ping_status] => open [post_password] => [post_name] => a-second-opinion-after-oms-trauma-care-leads-to-a-malpractice-lawsuit [to_ping] => [pinged] => [post_modified] => 2026-10-30 15:04:26 [post_modified_gmt] => 2026-10-30 19:04:26 [post_content_filtered] => [post_parent] => 0 [guid] => https://oms.medprodental.com/?p=8119 [menu_order] => 0 [post_type] => post [post_mime_type] => [comment_count] => 0 [filter] => raw ) [comment_count] => 0 [current_comment] => -1 [found_posts] => 64 [max_num_pages] => 22 [max_num_comment_pages] => 0 [is_single] => [is_preview] => [is_page] => [is_archive] => 1 [is_date] => [is_year] => [is_month] => [is_day] => [is_time] => [is_author] => [is_category] => 1 [is_tag] => [is_tax] => [is_search] => [is_feed] => [is_comment_feed] => [is_trackback] => [is_home] => [is_privacy_policy] => [is_404] => [is_embed] => [is_paged] => [is_admin] => [is_attachment] => [is_singular] => [is_robots] => [is_favicon] => [is_sitemap] => [is_posts_page] => [is_post_type_archive] => [query_vars_hash:WP_Query:private] => 439fb0764224d294cf8641b2c1283a0d [query_vars_changed:WP_Query:private] => [thumbnails_cached] => [allow_query_attachment_by_filename:protected] => [stopwords:WP_Query:private] => [compat_fields:WP_Query:private] => Array ( [0] => query_vars_hash [1] => query_vars_changed ) [compat_methods:WP_Query:private] => Array ( [0] => init_query_flags [1] => parse_tax_query ) [query_cache_key:WP_Query:private] => wp_query:351b7eaeebd798eba4709dbd4c5ecbc1 )

Additional Risk Tips content

When patients seek a second opinion after an unexpected outcome, even measured criticism from another provider can fuel doubt, escalate...
This OMS case study examines a wrong-tooth extraction and the critical role of accurate referrals, informed consent, and treatment verification.
Explore an OMS malpractice case study involving an All-on-4 implant procedure, surgical complications, clinical judgment, informed consent, and risk management lessons for implant dentistry.

This document does not constitute legal or medical advice and should not be construed as rules or establishing a standard of care. Because the facts applicable to your situation may vary, or the laws applicable in your jurisdiction may differ, please contact your attorney or other professional advisors if you have any questions related to your legal or medical obligations or rights, state or federal laws, contract interpretation, or other legal questions.

MedPro Group is the marketing name used to refer to the insurance operations of The Medical Protective Company, Princeton Insurance Company, PLICO, Inc. and MedPro RRG Risk Retention Group. All insurance products are underwritten and administered by these and other Berkshire Hathaway affiliates, including National Fire & Marine Insurance Company. Product availability is based upon business and/or regulatory approval and/or may differ among companies.

© MedPro Group Inc. All rights reserved.